



Why Cameras and Wearables Keep Failing Elderly Care — and What mmWave Radar Gets Right
Why Cameras and Wearables Keep Failing Elderly Care — and What mmWave Radar Gets Right

- Last Updated: November 17, 2026
Alinket Technology
- Last Updated: November 17, 2026
The pitch for aging in place sounds simple: keep older adults in their own homes, add sensors, and let technology flag trouble before it becomes tragedy. Falls, in particular, are the metric everyone watches — they are a leading cause of injury-related hospital visits for people over 65, and the ones that happen at night, alone, are the most dangerous.
Yet when families and care operators actually deploy monitoring, the two default tools — cameras and wearable panic buttons — keep hitting the same walls. Let's look at why, and at the sensing approach that is starting to replace both: 60 GHz millimeter-wave (mmWave) radar.
The Camera Problem is a Dignity Problem
Cameras are the obvious first instinct. They are cheap, familiar, and a single device can "see" a lot. But in a private home — and especially in a bathroom or bedroom — a camera is a constant witness. For the person being monitored, that erodes exactly the independence the system was meant to protect. In care facilities, wall-to-wall cameras raise consent, storage, and compliance questions that many operators are not equipped to handle.
There is also a technical ceiling. A camera needs enough light to interpret a scene, and "did that blur on the floor mean a fall or a dropped blanket?" is a hard inference to make reliably. Computer vision can help, but it inherits every bias of the dataset and still produces a video feed someone has to watch or store.
The Wearable Problem
Wearables — pendants, watches, fall-detecting bands — move the burden onto the person. They work only if the device is charged, worn, and worn correctly. The people at highest fall risk are often the least likely to remember a pendant or to keep a watch charged. And the highest-risk moments — showering, getting up at 3 a.m. to use the bathroom — are precisely when a wearable gets taken off.
Even when worn, many fall-detection wearables rely on accelerometers that struggle to tell a genuine fall from a sit-down or a bend. False alarms train people to ignore them; missed falls are worse.
What mmWave Radar Does
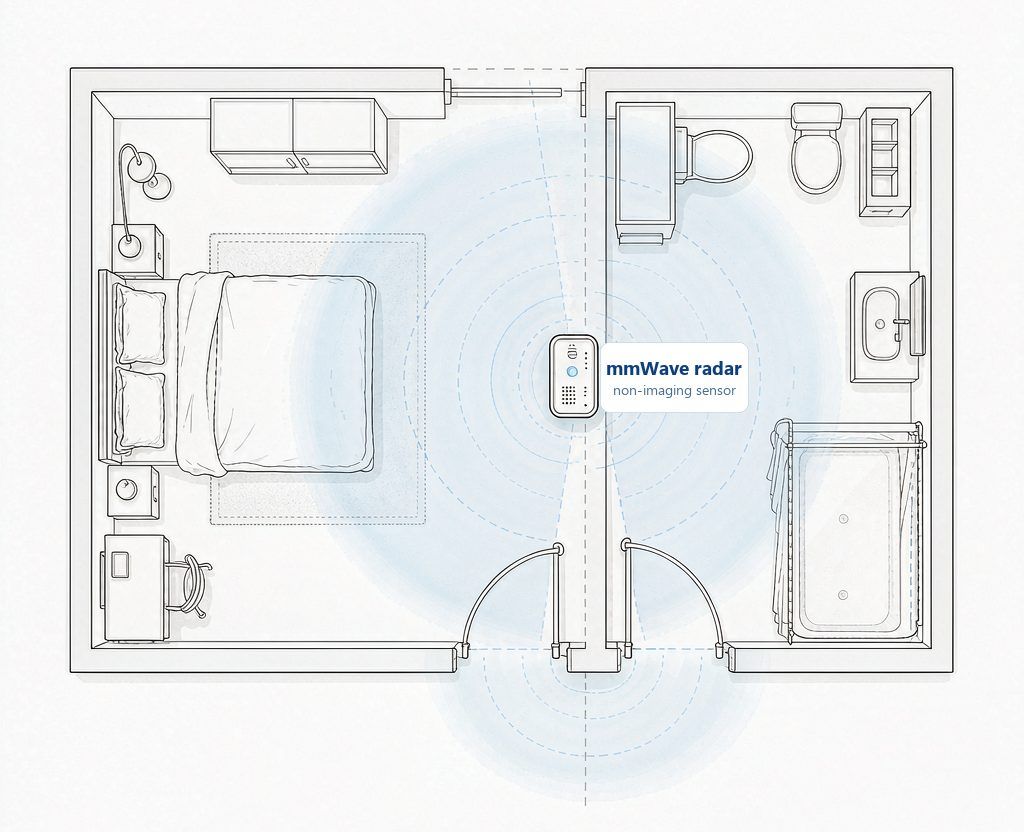
Millimeter-wave radar operates by emitting high-frequency radio waves (in the 60 GHz band, for the devices relevant here) and reading the echo. Because the wavelength is tiny, it can resolve sub-millimeter motion — the rise and fall of a chest as someone breathes, the micro-shifts of a body settling into a chair, the characteristic kinematics of a fall.
Two properties make it unusually well suited to care:
- It senses without an image. The device never captures a photo or video. What it produces is a stream of motion and range data — enough to know "a person fell" without ever knowing what the room looks like. For privacy, that is a different category of device from a camera.
- It senses without cooperation. No pendant, no charge cycle, no "remember to wear it." A ceiling- or wall-mounted unit covers a room continuously, including when the person is asleep or in the shower.
A 60 GHz FMCW (frequency-modulated continuous wave) radar can typically cover a 5–7 meter radius with a wide field of view, runs on a few watts, and is small enough to sit unobtrusively on a wall. Many units are rated for damp environments (IP54), which matters because the bathroom is one of the most fall-prone rooms in any home.

What it Can and Can't Tell You
Radar is excellent at motion and presence: fall detection, bed-exit and wandering alerts, prolonged inactivity, and even coarse vital signs like respiration and heart rate when the person is stationary. It is not a camera, so it cannot identify a face, read a label, or describe an object. For care monitoring, that limitation is usually a feature.
The honest trade-offs to design around:
- Placement matters. Height (commonly 1.4–2.2 m), angle, and what the beam passes through all change performance. A unit aimed at a swinging curtain will misbehave.
- False positives are a tuning problem, not a foregone conclusion. Pet movement, fans, and reflections need to be filtered in firmware. Vendors differ hugely here.
- Regulations vary. Radio-band approvals (e.g., FCC, CE, SRRC) and health-data handling rules differ by market. Buy for the market you ship in.
In the IoT stack
This is where the embedded-AI angle matters. A radar that only beamed raw signals to the cloud would be slow and bandwidth-hungry. The useful design puts inference on the device: the radar front end extracts features, a small microcontroller classifies the event ("fall," "bed exit," "normal"), and only the result — plus maybe a timestamp and a confidence score — travels over Wi-Fi or Bluetooth to a gateway and then to a dashboard.
That edge-inference pattern is what makes the system private (no raw sensor stream leaves the room), responsive (decisions in milliseconds, not round-trips), and cheap to run (tiny payloads). It is the same reason embedded AI is eating its way through industrial and medical sensing generally.
For teams building this, the integration surface is the part that bites: provisioning dozens of wall units, getting them onto the right network, and exposing events through an SDK so a care platform can act on them. That middleware — connect, provision, normalize, expose — is most of the real engineering, and it is where off-the-shelf radar chips meet the messy reality of deployed buildings.
Evaluating a Vendor
If you are specifying this for a care operator or a product, a short checklist:
- Ask for the false-alarm rate, not just the detection rate. Detection at 99% means little if alarms fire hourly.
- Confirm the environment rating. IP54 or better for bathrooms.
- Check the integration path. Is there an SDK? Does it speak MQTT or a standard cloud feed? Can you provision at scale?
- Verify the band approvals for your target markets.
- Pilot where risk is highest — bathrooms and night-time corridors — before a full rollout.
Non-contact radar will not replace human carers, and it is not the answer to every monitoring problem. But for the specific, recurring failures of cameras and wearables — privacy, dignity, and the simple fact that the highest-risk moments are the ones people are least able to cooperate with — it is the most credible fix we have shipped at scale. For builders evaluating the approach, the fastest path is a small pilot in the rooms where falls actually happen.

The Most Comprehensive IoT Newsletter for Enterprises
Showcasing the highest-quality content, resources, news, and insights from the world of the Internet of Things. Subscribe to remain informed and up-to-date.

New Podcast Episode

The State of LoRaWAN in 2026

Related Articles


Related Solutions
Portable Job Site Security and Safety
Secure construction sites from day one with portable, AI-powered video monitoring that moves with your crews.
Secure construction sites from day one with portable, AI-powered video monitoring that moves with your crews.
Iveda
Iveda

Asset Monitoring for Refrigeration Equipment
Protect refrigerated assets and maintain product quality with automated, real-time equipment monitoring.
Protect refrigerated assets and maintain product quality with automated, real-time equipment monitoring.
SmartSense by Digi
SmartSense by Digi
Infant Security for Hospitals
Enable immediate alerts, automated security responses, and mother-baby matching to reduce abduction risk.
Enable immediate alerts, automated security responses, and mother-baby matching to reduce abduction risk.
Vizzia Technologies
Vizzia Technologies

Related Solutions
Construction
Portable Job Site Security and Safety
Secure construction sites from day one with portable, AI-powered video monitoring that moves with your crews.
Iveda
Supply Chain & Logistics
Asset Monitoring for Refrigeration Equipment
Protect refrigerated assets and maintain product quality with automated, real-time equipment monitoring.
SmartSense by Digi
Healthcare
Infant Security for Hospitals
Enable immediate alerts, automated security responses, and mother-baby matching to reduce abduction risk.
Vizzia Technologies